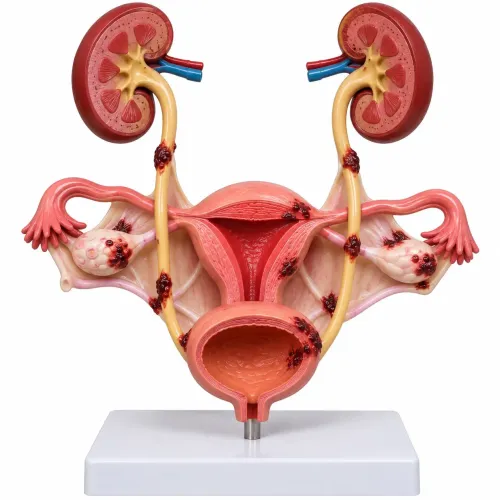
Pain with bowel movements and pelvic discomfort have several possible explanations, from constipation and haemorrhoids to inflammatory bowel disease and endometriosis. The timing, location and associated symptoms can help you decide how urgently to seek care, what information to record and which tests may clarify the cause.
Key takeaways
- Period-linked pain during bowel movements raises suspicion of bowel endometriosis.
- Seek urgent care for heavy rectal bleeding, severe pain, vomiting or bowel obstruction symptoms.
- Record bowel symptoms, menstrual timing, bleeding, medicines and previous test results.
- Ultrasound, MRI and colonoscopy examine different tissues, so their findings can differ.
Which symptom pattern points towards bowel endometriosis?
Painful bowel movements that begin before or during menstruation, alongside deep pelvic pain, make bowel endometriosis more suspicious than a routine bowel disorder. Dyschezia means pain during or just before passing stool; it is a key clue when it repeatedly worsens around your period. Bloating, diarrhoea, constipation, painful sex and rectal bleeding can also occur.
| Condition | Pattern that may help distinguish it |
|---|---|
| Bowel endometriosis | Dyschezia, deep cyclical pelvic pain, painful sex, bloating, diarrhoea or constipation; symptoms can persist all month when inflammation, fibrosis or narrowing affects the bowel. |
| IBS | Abdominal pain fluctuates with stool changes, diarrhoea, constipation or both, without a consistent menstrual pattern. |
| Constipation | Hard stools, straining and incomplete emptying usually drive the pain. |
| Anal fissure | Sharp, surface-level pain during or after stool, often with bright-red blood on the paper or stool. |
| Haemorrhoids | Bleeding, itching, swelling or discomfort around the anus. |
| Inflammatory bowel disease | Persistent diarrhoea, blood, weight loss or fever deserves medical assessment. |
A cyclical pelvic pain pattern raises suspicion, but it does not prove endometriosis. Bowel symptoms alone cannot diagnose it, and rectal bleeding is not required because lesions often involve the bowel’s outer or muscular layers rather than its inner lining. Seek assessment when symptoms recur, disrupt daily life or combine pelvic and bowel changes.
Which warning signs need urgent medical attention?
Heavy or substantial rectal bleeding, black stools, fainting or collapse needs urgent medical help. Do not assume these symptoms are caused by endometriosis or wait to see whether they match your menstrual cycle.
| Warning sign | What it can indicate | What to do |
|---|---|---|
| Heavy or substantial rectal bleeding | Significant bleeding or another gastrointestinal emergency | Seek immediate medical assessment |
| Black stools | Bleeding higher in the digestive tract | Attend urgent care, especially with weakness or dizziness |
| Persistent or repeated vomiting | Obstruction, infection or dehydration | Get urgent medical help |
| Inability to pass stool or gas | Bowel obstruction symptoms | Go to an emergency department |
| Marked abdominal swelling | Possible obstruction or severe inflammation | Seek urgent assessment |
| Severe or rapidly escalating severe abdominal pain | Obstruction, infection or another emergency | Do not wait for a routine appointment |
| Fever with severe pelvic or abdominal pain | Infection or an inflammatory emergency | Obtain immediate medical care |
| Fainting or collapse | Significant bleeding, shock or severe illness | Call emergency services |
A routine appointment is suitable for recurring, stable symptoms without these warning signs. Choose immediate care when pain is severe or worsening, vomiting continues, your abdomen becomes swollen, or you feel faint. A clinician must exclude dangerous causes before linking the symptoms to bowel endometriosis.
What should you record and expect during assessment?
Bring a symptom diary for endometriosis covering at least one menstrual cycle. It gives the clinician timing that memory often misses, especially whether bowel or bladder symptoms change with bleeding.
1. Record the cycle day, first and last day of bleeding, stool frequency, and Bristol stool type. Rate pain from 0 to 10 and note whether it starts before or during a bowel movement.
2. Note rectal bleeding, urinary symptoms, pain with sex, current medicines, previous pelvic surgery, and fertility concerns. Record whether symptoms occur only around menstruation or continue throughout the month.
3. Expect questions about pain location and depth: is it superficial at the anus or deep in the pelvis? The clinician will also ask whether constipation, diarrhoea, bloating, bowel pain, or bladder symptoms follow a cyclical pattern.
A pelvic examination may be appropriate, depending on your symptoms, consent, and clinical history. It can identify tenderness, nodules, or reduced organ movement, but a normal pelvic examination does not rule out endometriosis.
The usual imaging pathway includes a transvaginal endometriosis ultrasound performed by an experienced practitioner for endometriosis mapping. A pelvic MRI provides more detail when deep disease is suspected or surgery requires a clearer map of lesion extent and anatomy.
A normal scan does not exclude superficial endometriosis or every small-bowel lesion. Persistent, cycle-linked symptoms still warrant specialist assessment even when the pelvic examination, endometriosis ultrasound, or pelvic MRI is reported as normal.
Why can ultrasound, MRI and colonoscopy give different answers?
Ultrasound versus MRI for endometriosis produces different answers because each test sees different features. Specialist transvaginal ultrasound can map rectosigmoid endometriosis and other deep sites, including tenderness, adhesions and reduced movement. MRI can define deep disease, lesion extent and the surgical anatomy around the bowel, bladder and ureters.
Neither test perfectly excludes superficial or very small lesions.
| Test | What it shows best | What it can miss |
|---|---|---|
| Specialist transvaginal ultrasound | Deep nodules, adhesions and rectosigmoid involvement | Superficial or very small lesions |
| Pelvic MRI | Deep disease, bowel-wall depth, lesion extent and surgical anatomy | Tiny or superficial implants |
| Colonoscopy | The inner mucosal lining and accessible narrowing or masses | Disease outside the mucosa |
Colonoscopy bowel endometriosis is most useful when significant bleeding, a mass, inflammatory bowel disease or cancer needs investigation. A normal colonoscopy does not exclude endometriosis because the disease commonly grows on the serosa, the outer bowel surface, or the muscularis, the bowel’s middle layer, while leaving the mucosa normal.
An outer-surface lesion may cause pain or adhesions without entering the bowel wall. Bowel wall endometriosis can produce muscular thickening, narrowing, painful bowel movements or obstruction. Disease in the rectum or sigmoid colon may be called rectosigmoid endometriosis; its depth and length affect treatment, from surface shaving to full-thickness disc excision or segmental bowel resection.
When does bowel endometriosis need medication, surgery or a specialist team?
An imaging finding alone does not mean you need bowel endometriosis surgery. Doctors weigh disabling symptoms, lesion depth and size, bowel narrowing or obstruction, suspicious features, medication failure or intolerance, and your fertility plans.
For pain, continuous or cyclic combined hormonal contraception and progestogen treatment are common bowel endometriosis treatment options. This hormonal treatment can reduce hormone-related pain, but it cannot remove a fibrotic nodule or reverse an established stricture.
GnRH agonists or antagonists are usually considered after first-line treatment fails or causes unacceptable effects; many regimens include add-back therapy to reduce bone loss and menopausal-type symptoms.
| Approach | What it involves | Main trade-off |
|---|---|---|
| Shaving | Removes disease from the bowel surface | Preserves more bowel but can leave deeper disease |
| Disc excision | Removes a full-thickness circular section and closes the defect | Treats deeper invasion but carries leak, fistula and bleeding risks |
| Segmental resection | Removes a bowel segment and joins the ends | Used for extensive disease or stenosis; can alter bowel function and rarely requires a stoma |
Surgery is discussed for significant narrowing, obstruction, suspicious findings, disabling symptoms, or failed or intolerable medication—not simply because a scan shows a lesion. The decision also depends on whether the rectum or sigmoid is involved and how treatment affects fertility.
When surgery is under consideration, Endometriosis Surgeon in Pune can help coordinate an endometriosis-experienced gynaecological surgeon and colorectal surgeon. This matters when disease involves the rectum, sigmoid colon, ureters or bladder, or when fertility decisions must be made alongside bowel endometriosis surgery.
Related service
Bowel Endometriosis Endometriosis and Irritable Bowel Syndrome: Understanding the Double Struggle. View service → |
Frequently asked questions
Which symptom pattern points towards bowel endometriosis?
Pain during or before bowel movements that repeatedly worsens around menstruation, especially with deep pelvic pain, bloating, constipation, diarrhoea, painful sex or rectal bleeding, warrants assessment for bowel endometriosis.
Which warning signs need urgent medical attention?
Seek urgent medical care for severe or rapidly worsening abdominal pain, repeated vomiting, a swollen abdomen, inability to pass stool or gas, fainting, or heavy rectal bleeding.
What should you record before an assessment?
Record pain and bowel symptoms by menstrual-cycle day, stool changes, rectal bleeding, medicines, prior diagnoses, fertility concerns and copies of imaging or procedure reports.
Why can ultrasound, MRI and colonoscopy give different answers?
Ultrasound and MRI assess pelvic structures and the extent of deep disease in different ways, while colonoscopy examines the bowel lining; endometriosis often grows on or through the bowel wall without reaching that lining.
When does bowel endometriosis need medication, surgery or a specialist team?
Treatment depends on symptom severity, bowel involvement, fertility plans and response to medication. Deep disease, obstruction, significant bleeding or complex surgical anatomy calls for coordinated care from relevant specialists.